

BlogMedical claims
Why claims get denied, and how they get won back
Nearly one in five in-network claims was denied on HealthCare.gov plans in 2023. Here is how a claims specialist finds the real cause and turns a denial around.
Paul E. & Paul A., Founders · Nov 2, 2026 · 3 min read

A clinic sees a patient, sends the claim to the insurer, and waits. Weeks later the answer comes back: denied. Somewhere in a hospital or a revenue office, a claims specialist now has a stack of these, each with a code, an amount and a deadline.
This work is invisible to most people and essential to every provider. A denial that is never worked is revenue the clinic simply never receives.
KFF's analysis also found that consumers rarely appeal, and that public data often does not say why a claim was denied. On the provider side, the specialist's job is to find out.
Step 1: read the remittance, line by line
When an insurer (the payer) answers a claim, it sends a remittance advice. Each line carries a Claim Adjustment Reason Code (CARC), a standard code maintained by X12, plus a group code that says who is responsible for the difference. The code is the starting point, not the conclusion.
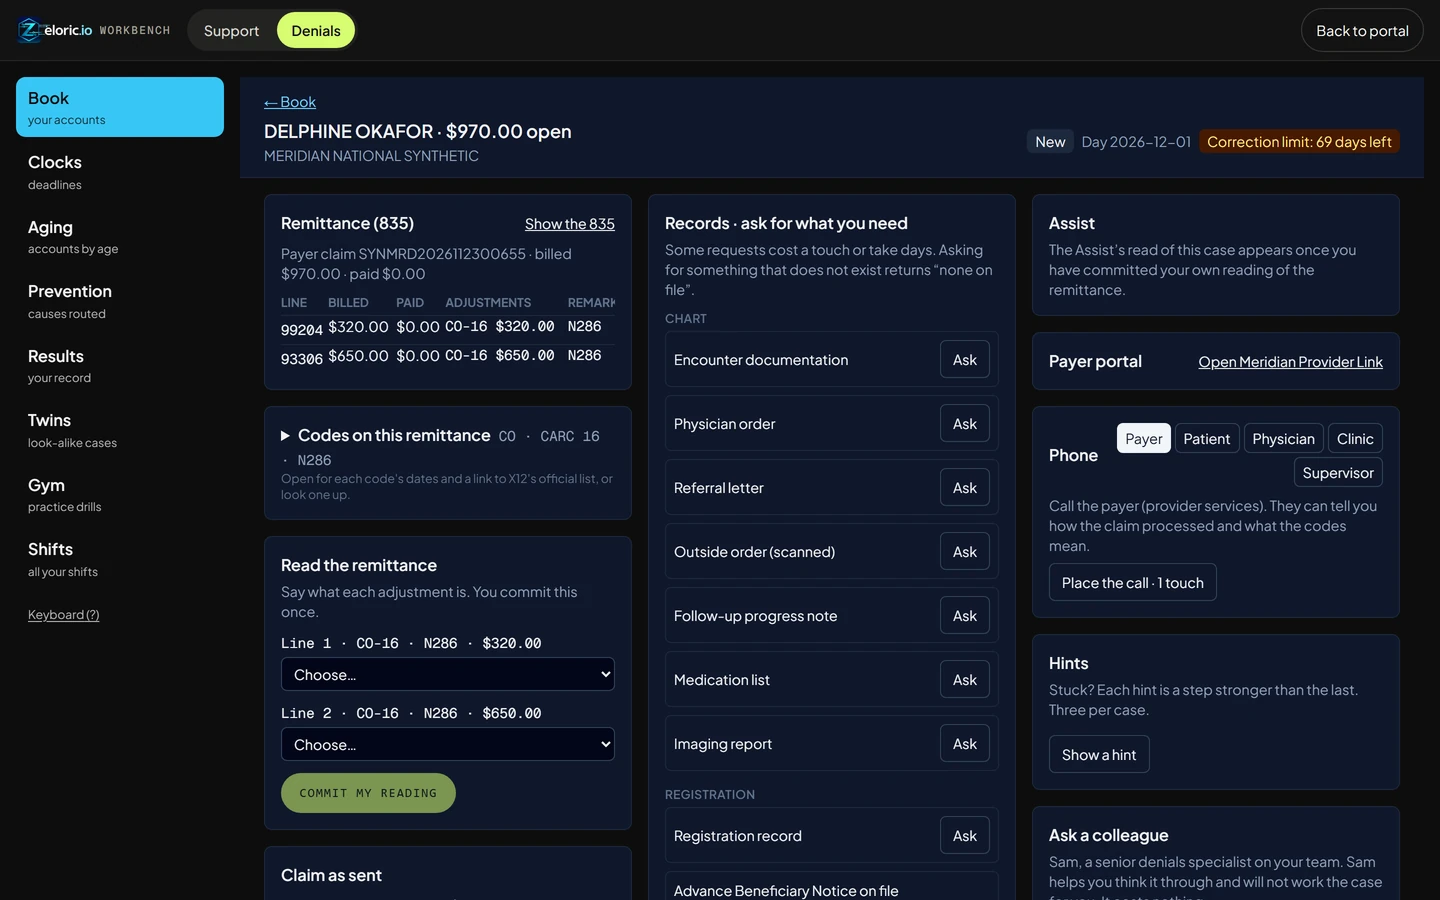
Read the code before you ask anyone, or any tool, what it means. The full list is public: X12 Claim Adjustment Reason Codes.
Step 2: find the real cause, not the label
A code says what the payer decided. It does not always say what went wrong upstream. Common real causes include:
- Eligibility: the patient's coverage had ended, or the claim went to the wrong plan
- Prior authorization: a service needed approval that was never obtained
- Coding: a diagnosis that does not support the procedure, or a missing modifier
- Duplicates: the same claim sent twice, often after a resubmission
- Timely filing: the claim reached the payer after its filing limit
Step 3: choose the best path the first time
Not every denial should be appealed. Some are fixed with a corrected claim. Some need a formal appeal with records. Some, honestly, are a loss to accept, and accepting it promptly is better than burning time on an appeal that cannot win.
- Correct and resubmit: a fixable error in the claim itself
- Appeal: the payer got it wrong, and you can show it
- Accept the loss: the denial is right, so close it cleanly
Step 4: keep every deadline alive
Payers set limits for corrected claims and appeals. Miss one and a winnable denial becomes a permanent write-off. Good specialists work their list by value and urgency, put anything close to its deadline first, and never leave a claim open without a next-action date.
For Medicare, the appeal levels and their time limits are published by CMS: Original Medicare appeals.
Step 5: write an appeal that wins
An appeal is an argument. It names the claim, the date of service and the denial by its code. It cites the payer's own policy by document, section and version. And it sends only the records that prove the point, not the whole chart.
A denial is a question from the payer. The appeal is your answer, with the evidence attached.
Getting into medical claims
Claims and denial specialists come from front-desk, medical billing, coding and customer service roles. Employers look for careful reading, comfort with codes and deadlines, and clear written appeals. To build those:
- Read how the work is judged in our Medical claims guide.
- Work a book of denied claims on the Medical claims desk, graded claim by claim and saved to your Shift Record.
Sources and further reading
#medical claims #healthcare #careers
Reading about the work is one thing. Doing it is how you show it. Your first ticket is free, with no account needed.
Try a realistic ticket free